Every fall I see the same headlines: “The 7 best Medicare Advantage plans.” I understand the appeal, but I don’t think a national ranking can tell you much. Medicare Advantage is sold county by county. The same insurer can run a strong plan in one county and a weak one an hour away, and the plan that’s right for your neighbor might not cover your cardiologist.
So this guide doesn’t rank insurers. It shows you how to find the best plan for you, in your ZIP code, for 2027. Open Enrollment runs October 15 to December 7, 2026, and new coverage starts January 1, 2027.
I’m a researcher who reads Medicare.gov, CMS documents and plan data for readers. I’m not a licensed insurance agent, and I don’t sell plans or get paid by insurers. For free, unbiased one-on-one help, call your State Health Insurance Assistance Program (SHIP). Everything below was checked against official sources on October 6, 2026.

If your current plan will not renew, read your Medicare Advantage plan is ending for 2027: key deadlines and next steps.
A few 2027 plans have a cap on how many people they will enroll. Read Medicare Advantage enrollment limits for 2027 before you pick a plan late in the season.
Before you compare plans, make sure your doctors are really in network for 2027. Here is how to check a Medicare Advantage provider directory and what the new directory law changes.
Medicare Advantage in 2027: the official numbers
CMS released its 2027 outlook on September 28, 2026. The short version is “stable”:
- The average monthly Medicare Advantage premium is projected to fall from $14.37 to $12.00.
- About 5,532 plans will be offered nationwide, almost the same as 2026.
- 97% of people with Medicare will have 10 or more plans to choose from.
- About 8 in 10 current members can stay in their plan at the same or a lower premium.
- Dental, vision and hearing extras are expected to stay about the same overall.
The federal ceiling on what a plan can make you pay rises too. For 2027, a plan’s in-network out-of-pocket limit can be as high as $9,850 (up from $9,250), or $14,800 for in- and out-of-network care combined, according to CMS’s final 2027 bid memo. Many plans set lower limits. KFF’s 2026 review of Medicare Advantage found the average in-network limit was $5,421.

Remember that you keep paying the Part B premium ($202.90 a month in 2026) on top of any plan premium. CMS hasn’t announced the 2027 Part B amount yet.
“Stable” on average still means changes for you
Averages hide a lot. Some plans are trimming extras like over-the-counter allowances and meal benefits, and some insurers are leaving counties altogether. If your plan is ending, you’ll get a notice and a special window to choose a new one; our guide to the Clear Spring Health exit walks through how that works. For plans that are staying, our Medicare Advantage benefit cuts checklist shows where reductions tend to hide in the Annual Notice of Change.
A few other 2027 changes worth knowing:
- Prior authorization is getting faster and more digital. Since January 2026, CMS rules require Medicare Advantage plans to decide urgent requests within 72 hours and standard requests within 7 calendar days, and to give a specific reason for a denial. Medicare says that starting in 2027, plans may be able to process requests electronically, with decisions in your patient portal.
- Flex and benefit cards are tighter. CMS’s 2027 final rule requires plan debit cards to be linked to covered items at the register and limited to the plan year.
- Agents have fewer timing limits. The same rule removed restrictions on when and how you can talk with licensed agents and brokers. Expect more calls and mailers this fall. Medicare itself won’t call you to sell a plan.
- Drug costs are capped at $2,400 for Part D coverage inside Medicare Advantage plans, the same as stand-alone plans. Our 2027 Part D guide explains what’s happening to drug premiums.
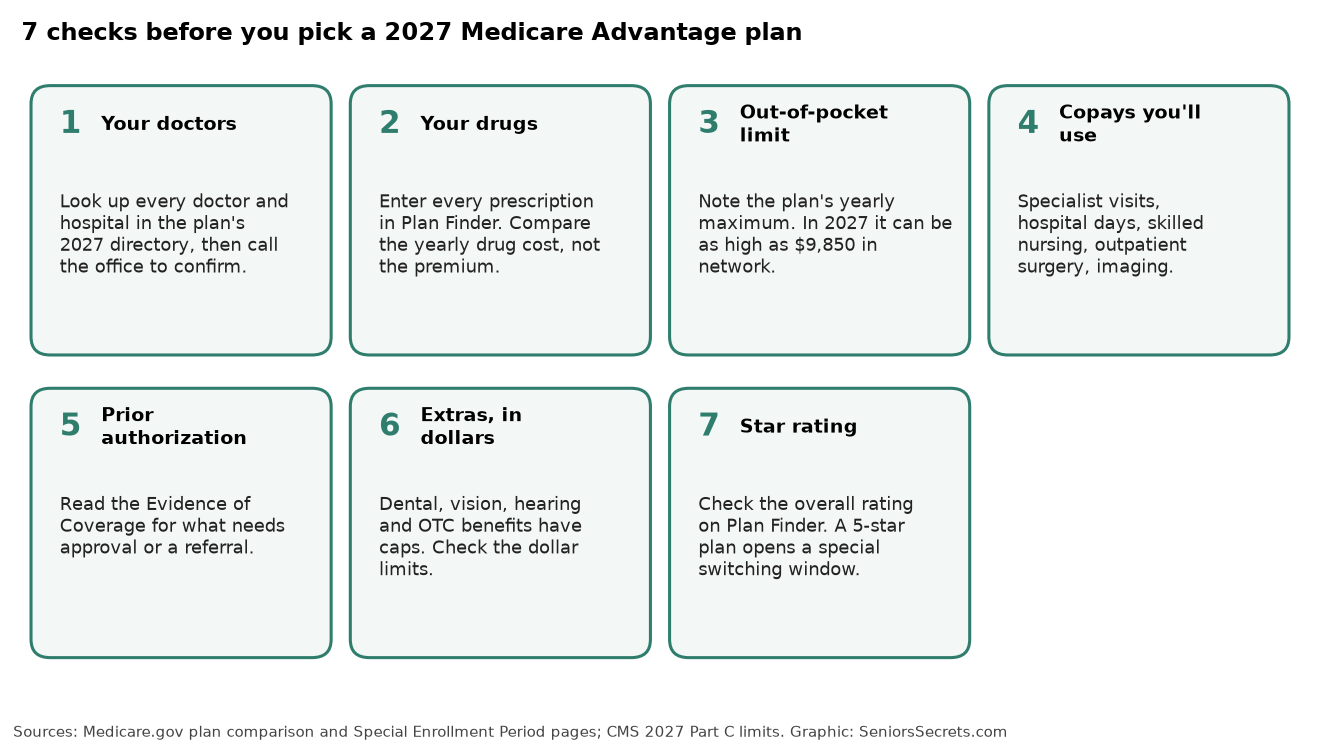
7 checks before you pick a plan
This is the part that actually decides whether a plan is “best” for you.
- Your doctors and hospitals. Look up each one in the plan’s 2027 directory, then call the office and ask, “Will you be in network with this plan in 2027?” Directories can be out of date.
- Your drugs. Enter every prescription and dose in Plan Finder at Medicare.gov and compare the estimated yearly drug cost, not just the premium.
- The out-of-pocket limit. Write down each plan’s yearly maximum. This is your worst-case number for medical care in a bad year.
- The copays you’ll really use. Specialist visits, a hospital day, skilled nursing, outpatient surgery, MRIs, physical therapy. A $0 premium plan with a $400-a-day hospital copay is a very different plan from one with $250.
- Prior authorization and referrals. HMOs usually need referrals; most plans need prior approval for some services. The Evidence of Coverage spells it out.
- Extras, in dollars. “Dental included” can mean two cleanings a year or $2,000 toward crowns. Check the dollar caps and the networks for dental, vision and hearing.
- The star rating. Ratings run from 1 to 5 stars and are based on quality and member experience. More on these below.
My honest view: the premium is the least important number on the page. The two that matter most are whether your doctors are in network and the out-of-pocket limit, because those decide what a bad year looks like.
The main plan types, in plain English
Medicare’s health plan options page lists these Medicare Advantage types:
- HMO: You generally use the plan’s network and need referrals to see specialists. Usually the lowest premiums.
- PPO: You can go out of network for covered care, but you’ll pay more. Usually no referrals.
- Special Needs Plans (SNPs): For people with certain chronic conditions, people living in an institution, or people with both Medicare and Medicaid (D-SNPs). If you have Medicaid too, our D-SNP guide is the place to start.
- PFFS and Medical Savings Account (MSA) plans: Less common, with their own payment rules. Read the plan materials closely.
How star ratings work, and the 5-star window
CMS rates plans every year on clinical quality, member experience and customer service. New ratings appear on Plan Finder in early October. CMS published the 2027 Star Ratings fact sheet on October 8, 2026: about 37% of Medicare Advantage drug plan (MA-PD) contracts (188) earned 4 stars or higher for 2027, covering about 71% of MA-PD enrollees. (For comparison, the 2026 fact sheet had reported about 40% of contracts and 64% of members in 4+ star plans.) Our 2027 Medicare Star Ratings guide explains how to use the scores during Open Enrollment without treating them as the only decision factor.
Two rules make ratings more than a gold sticker, per Medicare’s Special Enrollment Periods page:
- If a 5-star plan is offered where you live, you can switch into it once between December 8 and November 30 of the following year, outside Open Enrollment.
- If your plan has had fewer than 3 stars for 3 years in a row, you get a special chance to switch.
A high rating doesn’t replace the seven checks above. A 5-star plan that doesn’t include your oncologist isn’t the best plan for you.

When you can enroll or switch
From Medicare’s joining-a-plan rules:
- Open Enrollment, October 15 to December 7, 2026: join, switch or drop a Medicare Advantage plan, or move between Medicare Advantage and Original Medicare. Changes start January 1.
- Medicare Advantage Open Enrollment, January 1 to March 31, 2027: if you’re already in a Medicare Advantage plan, you can switch to another one once, or drop it and go back to Original Medicare (and join a drug plan).
- Special Enrollment Periods: moving, losing other coverage, getting Medicaid or Extra Help, a plan leaving your area, and the 5-star rule above.
One warning I repeat every year: if you’re thinking about Original Medicare instead, check Medigap first. Outside your guaranteed-issue windows, a Medigap insurer can ask health questions. Our Medicare Advantage vs Original Medicare comparison covers the Medigap rules and who tends to do better with each.
Where to enroll
- Plan Finder at Medicare.gov or 1-800-MEDICARE (1-800-633-4227), open 24 hours a day, 7 days a week.
- Directly with the plan, by phone or on its website.
- A licensed agent or broker. They can save you time, but they’re usually paid by the insurers they represent and may not offer every plan in your area. Ask which companies they work with.
- Your SHIP counselor, who is free and doesn’t sell anything. If you only call one person this fall, I’d make it them.
FAQ
What is the best Medicare Advantage plan for 2027?
There isn’t one national answer. The best plan for you covers your doctors and drugs, has an out-of-pocket limit you could afford in a bad year, and has solid quality ratings in your county. Compare at least two or three plans in Plan Finder.
Is a 5-star plan always the best choice?
No. It’s a good sign of quality, and it gives you a special switching window, but it still has to include your providers and cover your prescriptions at a reasonable cost.
What’s the most I could pay in a Medicare Advantage plan in 2027?
For covered medical care, no more than $9,850 in network, or $14,800 combined in and out of network, plus premiums. Drug costs have a separate $2,400 cap. Many plans set lower medical limits.
Can I change my mind after January 1?
Yes, once. During the Medicare Advantage Open Enrollment Period (January 1 to March 31, 2027) you can switch to another Medicare Advantage plan or return to Original Medicare.
Do I still pay the Part B premium with Medicare Advantage?
Yes. Some plans include a “giveback” that lowers your Part B premium, but it’s usually a modest amount. Our Medicare giveback guide explains how to find those plans.
Facts checked against Medicare.gov, CMS and KFF on October 6, 2026. The 2027 Part B premium was not yet published as of October 9, 2026; 2027 Star Ratings were published October 8, 2026 and are reflected above. This page will be updated again when Part B amounts are posted. This article is for education, not personal insurance advice.
Related guides