Medicare Hospice Coverage: Who Qualifies, What It Pays For, What It Doesn’t, and How Families Choose a Provider

Medicare Part A covers hospice care for people with a terminal illness and a life expectancy of six months or less who choose comfort care instead of treatment to cure the illness. For most families, covered hospice care costs nothing, apart from a copay of up to $5 per prescription for pain and symptom drugs and a small share of respite care.
That’s the short version. The details matter, because they decide what you’ll pay for room and board, what happens if your loved one lives longer than six months, and what to do if the care isn’t working.
I’m a researcher, not a medical professional or a licensed agent. Everything below comes from Medicare.gov’s hospice coverage page and Medicare’s official hospice booklet, linked below. A hospice team, your doctor, or your State Health Insurance Assistance Program (SHIP) can help with your specific situation.
Who qualifies for Medicare hospice
You must have Medicare Part A and meet all three conditions:
- A doctor certifies a terminal illness. Your hospice doctor and your regular doctor, if you have one, certify that you’re terminally ill, with a life expectancy of six months or less if the illness runs its normal course.
- You accept comfort care. You choose palliative care, meaning care focused on comfort and symptoms, instead of care to cure the terminal illness and related conditions.
- You sign an election statement. You sign a statement choosing hospice instead of other Medicare-covered treatment for the terminal illness.
The six-month estimate is a doctor’s judgment, not a deadline. If a person lives longer, hospice can continue, as explained below. And choosing hospice isn’t a one-way door. You can stop hospice at any time and go back to regular Medicare coverage.
What Medicare hospice covers
Once hospice starts, the benefit is meant to cover everything needed for the terminal illness and related conditions. The hospice team sets up a plan of care with you and your family. Covered services include:
- Doctor and nursing services
- Medical equipment, like a hospital bed, wheelchair or walker
- Medical supplies, like bandages and catheters
- Drugs for pain relief and symptom control
- Hospice aide and homemaker services
- Physical and occupational therapy, and speech-language pathology
- Social work services
- Dietary counseling
- Grief and loss counseling for the patient and family
- Short-term inpatient care for pain and symptoms that can’t be managed at home
- Short-term inpatient respite care, so family caregivers can rest
Care usually happens wherever the person lives: their home, an assisted living facility, or a nursing home.
What it costs
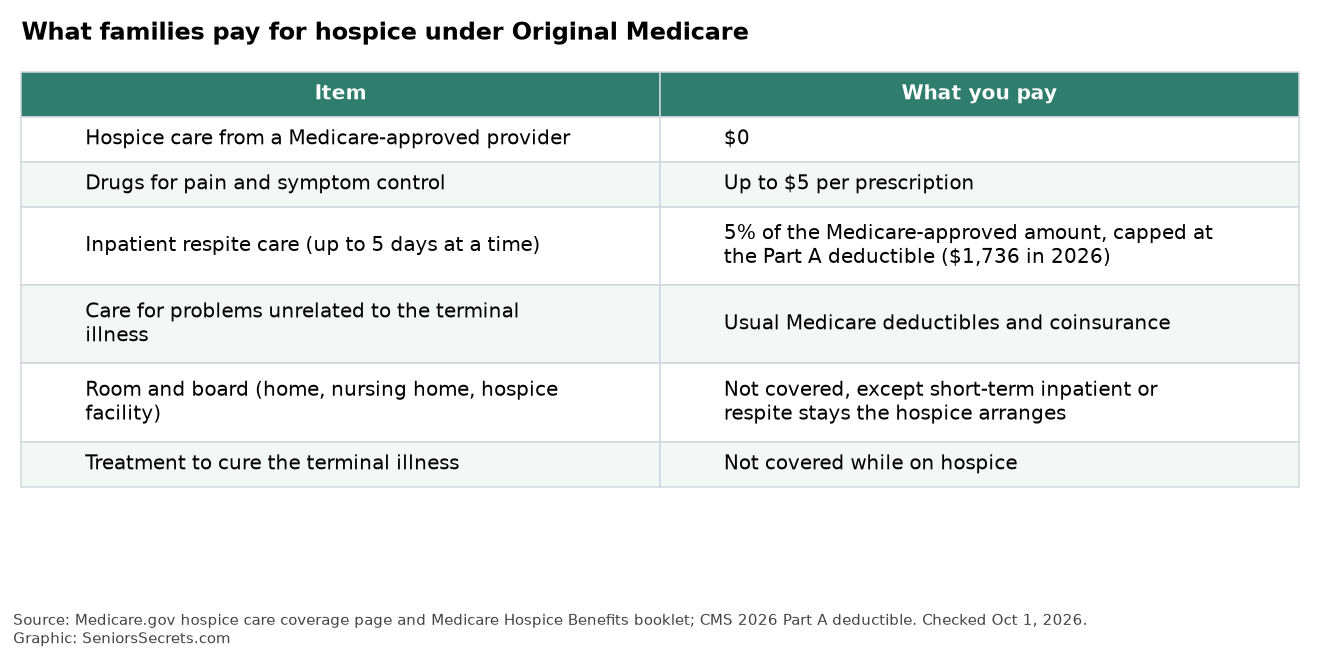
| Item | What you pay with Original Medicare |
|---|---|
| Hospice care from a Medicare-approved provider | $0 |
| Outpatient drugs for pain and symptom management | Up to $5 per prescription |
| Inpatient respite care | 5% of the Medicare-approved amount, capped at the Part A deductible ($1,736 in 2026) |
| Care for health problems unrelated to the terminal illness | Usual Medicare deductibles and coinsurance |
| Room and board at home, in a nursing home or in an inpatient hospice facility | Not covered, except for short-term inpatient or respite stays the hospice arranges |
The room-and-board gap
This is the most common surprise. Medicare doesn’t pay room and board for hospice patients, whether they live at home, in a nursing home or in an inpatient hospice facility. The exception is short-term inpatient or respite care that the hospice team arranges.
If your loved one lives in a nursing home and switches to hospice, the hospice covers the hospice care, but the monthly nursing home bill for room and board continues. Medicaid may help pay it if your loved one qualifies. My guide to Medicaid spend-down explains how people with too much income can still qualify.
What Medicare won’t cover once hospice starts
According to Medicare.gov, once the hospice benefit starts, Medicare won’t pay for:
- Treatment intended to cure the terminal illness or related conditions.
- Prescription drugs to cure the illness, as opposed to drugs for comfort.
- Care from a hospice provider your hospice team didn’t set up. All care for the terminal illness must come from or be arranged by your chosen hospice. You can still keep your regular doctor or nurse practitioner as your attending provider.
- Emergency room visits, inpatient hospital stays or ambulance rides unless the hospice team arranges them or they’re unrelated to the terminal illness.
That last point catches families during a crisis. Call the hospice team first, day or night, before calling 911 or going to the ER, unless it’s clearly unrelated to the terminal illness. Otherwise you could owe the full cost.
You can ask the hospice for a written list of items, services and drugs it has decided aren’t related to the terminal illness, with reasons. The hospice must give it to you within 3 to 5 days of your request.
How long hospice lasts: benefit periods
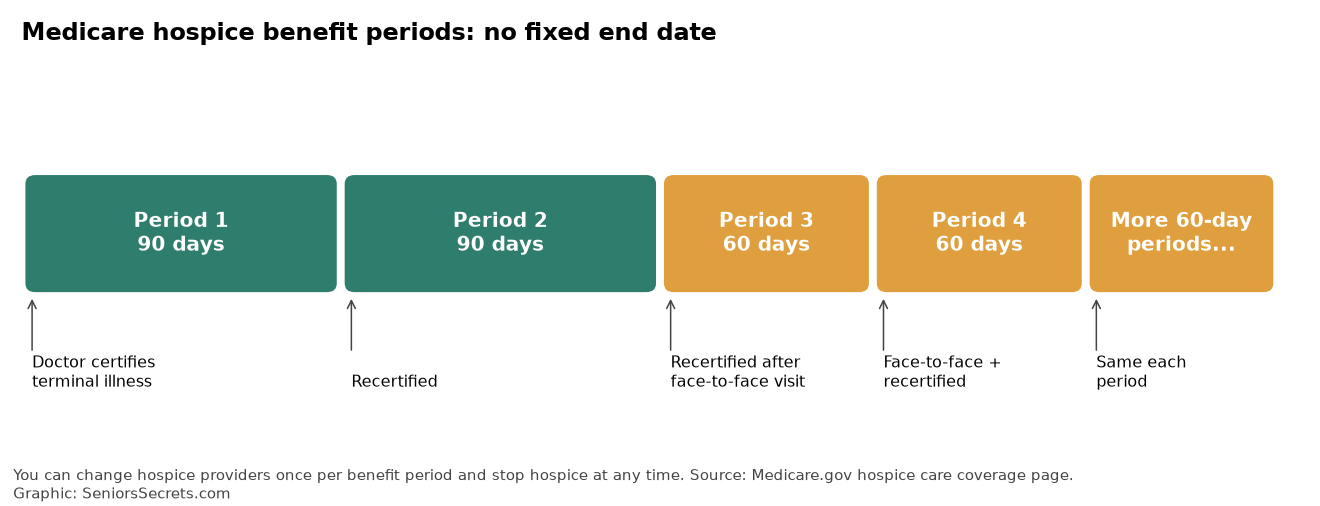
Medicare covers hospice in benefit periods: two 90-day periods, followed by an unlimited number of 60-day periods. At the start of each period, the hospice doctor recertifies that the person is still terminally ill. Before the third period and every period after that, a hospice doctor or nurse practitioner must see the person face to face.
In practice, people sometimes improve on hospice, and their doctor may decide they no longer qualify. That’s called a “live discharge.” The person goes back to regular Medicare and can return to hospice later if their condition changes.
Respite care for family caregivers
If the main caregiver needs a break, hospice can arrange a short inpatient stay in a Medicare-approved facility. Medicare’s hospice benefits booklet says respite stays can last up to 5 days at a time, and you can get respite care more than once. You pay 5% of the Medicare-approved amount.
Caregiving at the end of life is exhausting. If you’re the caregiver, look at the National Family Caregiver Support Program, which offers more respite and support, and watch for the signs of caregiver burnout.
Hospice if you have Medicare Advantage
If you’re in a Medicare Advantage plan, Original Medicare pays for hospice, not your plan. You don’t have to leave your Medicare Advantage plan. It can still cover services unrelated to the terminal illness and any extra benefits it offers, like dental or vision. You can use any Medicare-approved hospice, not just one in your plan’s network.
How to choose a hospice provider
Families often have to choose quickly, sometimes from a hospital bed. A few steps help:
- Ask the doctor or hospital discharge planner for names, but remember you get to choose. A hospital or doctor can’t require a specific hospice.
- Check Medicare’s Care Compare tool. The hospice section of Medicare Care Compare shows family survey ratings and quality measures for Medicare-approved hospices near you.
- Ask each hospice the same questions:
- How quickly can you start care, including on weekends?
- How fast does a nurse come at night if symptoms get worse?
- How often will the nurse and aide visit?
- Which medicines and equipment do you provide, and which won’t you cover?
- Do you have your own inpatient unit, or where would you send us for inpatient or respite care?
- What grief support do you offer families afterward?
- Get the answers in writing, including any items the hospice says it won’t cover.
Changing hospice or stopping hospice
You can change hospice providers once during each benefit period. You can also stop hospice at any time, for example to try a new treatment, by signing a revocation form. Regular Medicare coverage resumes, and you can elect hospice again later.
If the hospice tells you it’s ending your care because you no longer qualify, you have the right to a fast appeal through your Quality Improvement Organization. My guide to Medicare appeals explains the deadlines, which are measured in hours.
Hospice and planning ahead
Hospice works best when families have talked about wishes before a crisis. An advance directive records what kind of care someone wants and who should make decisions if they can’t. Most states offer free forms, and you don’t need a lawyer.
Hospice isn’t the same as palliative care in general. Palliative care focuses on comfort and can be given alongside treatment to cure an illness, at any stage. Hospice is palliative care for people who have decided to stop curative treatment.

FAQ
Does Medicare pay for hospice in a nursing home?
Medicare pays for the hospice care itself in a nursing home, but not room and board. Families or Medicaid usually cover the nursing home’s daily charge.
What if my loved one lives longer than six months?
Hospice can continue. After the two 90-day periods, there are unlimited 60-day periods as long as a doctor recertifies the terminal illness after a face-to-face visit.
Can you leave hospice and go back to treatment?
Yes. You can stop hospice at any time, return to regular Medicare coverage, and elect hospice again later if you qualify.
How much does hospice cost with Medicare?
Usually nothing for the hospice care itself. You may pay up to $5 per prescription for comfort drugs and 5% of the approved amount for inpatient respite care.
Can I keep my own doctor on hospice?
Yes. You can name your regular doctor or nurse practitioner as your attending provider, who works with the hospice team.
Related guides